
Diabetes changes the way the body fights infection and heals wounds, which makes bone infections far more dangerous for diabetic patients than for the general population. One of the more serious complications that can develop is an osteomyelitis fistula: a draining tunnel that forms between an infected bone and the skin surface. Understanding how Osteomyelitis Fistulas develop, what warning signs to watch for, and how they’re treated can help patients and caregivers catch the problem early, when treatment is most effective.
What Is an Osteomyelitis Fistula?
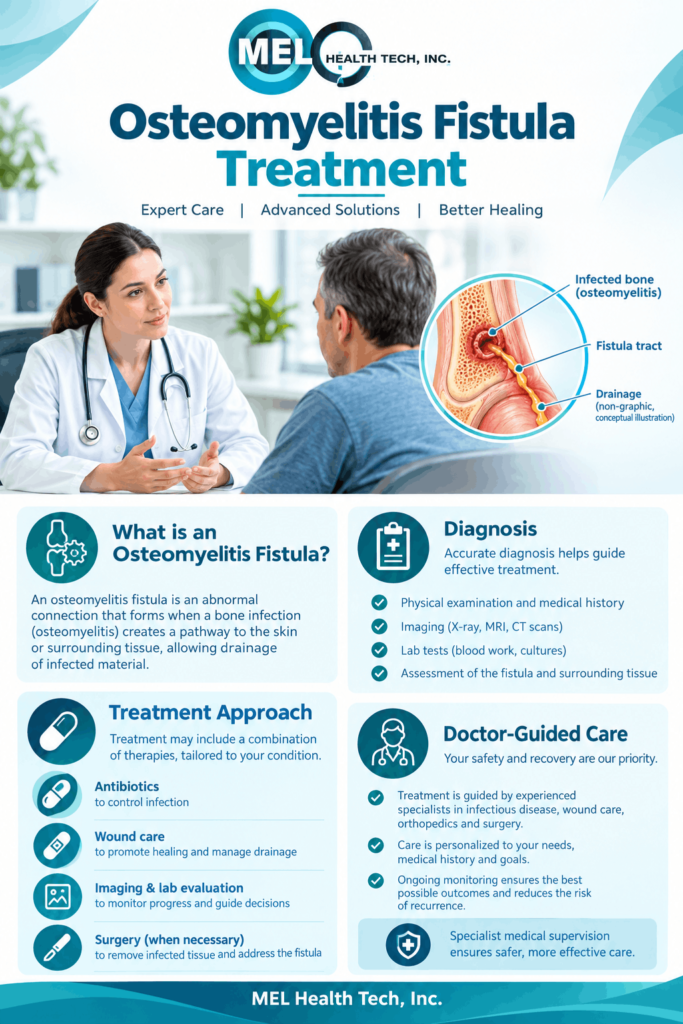
Osteomyelitis is an infection of the bone, usually caused by bacteria that reach the bone through the bloodstream, a wound, or a nearby soft-tissue infection. When osteomyelitis becomes chronic and isn’t fully treated, the body sometimes forms a fistula: an abnormal channel that allows pus and infected material to drain from the bone out through the skin.
In diabetic patients, this most often happens in the feet, particularly in cases of diabetic foot ulcers that progress untreated. Because diabetic neuropathy can dull pain sensation, a bone infection can advance significantly before a person even notices something is wrong.
Why Diabetic Patients Are at Higher Risk
Several factors specific to diabetes increase the likelihood of osteomyelitis progressing to a fistula:
- Peripheral neuropathy reduces sensation in the feet, so wounds and infections can go unnoticed for weeks.
- Poor circulation (peripheral vascular disease) limits blood flow to the extremities, slowing the delivery of immune cells and antibiotics to the infection site.
- Elevated blood sugar impairs white blood cell function, making it harder for the body to clear bacteria.
- Delayed wound healing means minor cuts or ulcers stay open longer, giving bacteria more opportunity to reach the bone.
Because of this combination, diabetic foot infections are one of the leading causes of chronic osteomyelitis and, by extension, fistula formation.
Recognizing the Symptoms
Since pain may not be a reliable warning sign in diabetic patients, it’s important to watch for other indicators:
- A wound, ulcer, or sore that isn’t healing, especially on the foot
- Persistent or recurring drainage of pus or fluid from a skin opening
- Redness, warmth, or swelling around a wound
- A visible sinus tract or small opening in the skin that continually drains
- Fever, chills, or general fatigue in more advanced infections
- A foul odor from the wound site
- Exposed bone visible at the base of an ulcer
Any combination of these symptoms in a diabetic patient warrants prompt medical evaluation. Untreated, the infection can spread further into the bone and surrounding tissue, increasing the risk of amputation.
How Osteomyelitis Fistulas Are Diagnosed
Diagnosis typically involves a combination of:
- Physical examination of the wound and surrounding tissue
- Imaging, such as X-ray, MRI, or CT scan, to assess how far the infection has spread into the bone
- Blood tests, including inflammatory markers like ESR and CRP
- Wound or bone cultures to identify the specific bacteria causing the infection, which guides antibiotic selection
- Probe-to-bone testing, where a clinician gently probes the wound to check whether it reaches the bone
Treatment and Care Options
Treatment depends on how advanced the infection is, but generally includes some combination of the following:
Antibiotic therapy. Long courses of targeted antibiotics, often lasting several weeks, are used to control the infection. In more severe cases, IV antibiotics may be needed.
Surgical debridement. Dead or infected bone and tissue are surgically removed to allow healthy tissue to heal and to reduce the bacterial load.
Wound care. Regular dressing changes, specialized wound care techniques, and sometimes negative pressure wound therapy help the fistula tract close and promote healing.
Blood sugar management. Tight glucose control is essential during treatment, since elevated blood sugar directly interferes with the body’s ability to fight infection and heal.
Vascular assessment. If poor circulation is contributing to the problem, a vascular specialist may need to evaluate whether blood flow to the area can be improved.
Ongoing monitoring. Even after visible symptoms resolve, diabetic patients typically need continued follow-up, since chronic osteomyelitis can recur if not fully cleared.
At Mel Health Tech, we work to help patients and providers better understand and manage complex conditions like diabetic osteomyelitis fistulas through accessible, evidence-informed health information and care resources.
Prevention Tips for Diabetic Patients
- Check feet daily for cuts, blisters, redness, or swelling, especially if neuropathy is present
- Keep blood sugar levels within your target range as consistently as possible
- Seek medical care immediately for any foot wound that isn’t healing within a few days
- Wear properly fitted footwear to reduce friction and pressure points
- Attend regular podiatry checkups, particularly if you have a history of foot ulcers or neuropathy
FAQ
Q: What is the difference between osteomyelitis and an osteomyelitis fistula?
A: Osteomyelitis is the underlying bone infection itself. A fistula is a complication that can develop when that infection becomes chronic, creating a draining channel from the bone to the skin surface.
Q: Can an osteomyelitis fistula heal without surgery?
A: In some cases, especially when caught early, antibiotics and wound care alone may be enough. However, many chronic cases require surgical removal of infected bone tissue before the fistula can fully close.
Q: Is amputation always necessary for diabetic patients with this condition?
A: No. Amputation is generally considered only when infection is extensive, blood flow cannot be restored, or other treatments have failed. Early diagnosis significantly reduces this risk.
Q: How long does treatment usually take?
A: Antibiotic courses often run four to eight weeks or longer, and full healing of the fistula tract can take additional time depending on wound severity and how well blood sugar is controlled during recovery.
Q: Who should diabetic patients see if they suspect a bone infection?
A: A primary care physician, podiatrist, or infectious disease specialist can evaluate symptoms. Cases involving exposed bone or non-healing ulcers are often referred to a wound care or orthopedic specialist.
Conclusion
Osteomyelitis Fistulas represent a serious but manageable complication for diabetic patients when caught early. Because diabetes can mask the usual warning signs of infection, staying alert to non-healing wounds, unusual drainage, and other subtle symptoms is critical. With prompt diagnosis, targeted antibiotic therapy, proper wound care, and consistent blood sugar management, most patients can achieve meaningful healing and avoid more serious complications.